

There is no single best probiotic for gastritis, and any article that hands you one product name is skipping the part that decides the answer. Gastritis has several distinct causes, and nearly all of the human trial evidence on probiotics in this area comes from people being treated for Helicobacter pylori, where the outcomes measured were eradication rates and antibiotic side effects, not stomach pain.
That mismatch explains why product lists read so confidently and help so little. A strain and dose that improved eradication rates in an antibiotic trial is not automatically the right choice for someone whose stomach irritation comes from a painkiller or for someone with an autoimmune condition that a supplement cannot touch. What follows works through the evidence in the order a pharmacist would: what the trials showed, how the cause of your gastritis changes the decision, how to check a label, where the side-effect benefit is real, which symptoms mean stop and call a doctor, and what to raise at your appointment.
Table of Contents
- Why No Single Probiotic Is Best for Gastritis
- Trial Results for Probiotics Added to H. pylori Treatment
- Gastritis Causes That Change Your Probiotic Choice
- How to Judge a Probiotic Label for Gastritis
- What Probiotics Can and Cannot Do for Antibiotic Side Effects
- Red Flags That Need a Doctor, Not a Supplement
- Talk to Your Doctor Before Buying a Probiotic for Gastritis
- Frequently Asked Questions
Why No Single Probiotic Is Best for Gastritis
The strongest available summary of the evidence says the same thing. The World Gastroenterology Organisation's guidance on probiotics and prebiotics reports that the 2022 Maastricht VI/Florence consensus found certain probiotics can reduce gastrointestinal side effects from H. pylori eradication therapy and may modestly improve treatment outcomes. It also grades that finding with caution: the evidence quality was weak and the recommendation only moderate.
The same guidance is blunt about the limits. No evidence supports using a probiotic alone, without antibiotics, to eradicate H. pylori. That matters because H. pylori is a major infectious cause of chronic gastritis and can contribute to peptic ulcer disease and gastric cancer. A supplement that cannot clear the bacterium is not a substitute for testing, prescribed antibiotics, or acid suppression.
Probiotic effects in these trials appear to come mainly from improved treatment tolerability and, potentially, better adherence. People who feel less sick on a two-week antibiotic course are more likely to finish it, and finishing it is what drives eradication. The bacterium is not being reliably eliminated by the probiotic itself.
The practical rule: a probiotic is never the treatment for gastritis. It is, at most, an addition to one specific treatment, and only when that treatment is underway.
Three things separate a defensible purchase from a hopeful one:
- A named, clinically studied strain. Not a genus, not a blend total. A specific strain or strain combination that appears in human research.
- A dose that matches that research. The CFU count on the front of the bottle is a marketing number until it lines up with what the trial used.
- A defined role alongside medical care. Adjunct to eradication therapy, or support during antibiotic treatment. Nothing broader.
The rest of this article follows that logic: the pooled trial data first, then the causes of gastritis, then the label checks, the side-effect evidence, the red flags, and the conversation with your doctor that should come before any purchase.
Trial Results for Probiotics Added to H. pylori Treatment
Four pooled analyses tell the story better than any single study, because the pattern repeats across different trial sets, populations and antibiotic regimens.
| Study | With probiotic | Control | Regimen |
|---|---|---|---|
| Meta-analysis, 23 trials (3,900 people) | 80.74% | 72.26% | Triple therapy plus probiotic vs triple therapy alone |
| Meta-analysis, 45 trials (6,997 participants) | 82.31% | 72.08% | Standard eradication therapy with or without probiotic |
| Frontiers in Microbiology review, 12 trials (2,144 participants) | 80.34% | 70.49% | Probiotic pretreatment vs control treatment |
| Medicine review, 10 trials (1,630 patients) | 88.78% | 81.27% | Bismuth quadruple therapy with or without probiotic |
Read the first row slowly. A meta-analysis of 23 randomized trials covering 3,900 people found eradication in 80.74% of those given triple therapy plus a probiotic against 72.26% of those given triple therapy alone, with 1,874 people in the probiotic group and 2,026 in the control group (the 23-trial meta-analysis). The 45-trial analysis of 6,997 participants lands in nearly the same place, 82.31% versus 72.08% (Archives of Microbiology meta-analysis).
The 2025 Frontiers in Microbiology review, pooling 12 trials and 2,144 participants, found 80.34% eradication with probiotic pretreatment against 70.49% for control treatment (Frontiers in Microbiology systematic review). The newest of the four, a Medicine review of 10 trials and 1,630 patients, tested probiotics added to bismuth quadruple therapy and saw eradication rise from 81.27% to 88.78%, an absolute gain of 7.5 percentage points (Medicine systematic review). That analysis also coded treatment failure and reported an odds ratio of 0.58 with a 95% confidence interval of 0.50 to 0.68 favoring supplementation, while the trials recorded less nausea, diarrhea, epigastric pain, vomiting, taste distortion and skin rash, though appetite loss was similar in both groups (probiotics added to triple therapy).
What the gap between the columns actually means
The gains are real and consistent, roughly 7 to 10 percentage points across analyses. They are also not universal. A person in one of these trials could still fail treatment while taking a probiotic, and the control groups cleared the infection most of the time without one.
Results shift with strain, dose, antibiotic regimen, population and local antibiotic resistance patterns. None of these analyses identifies one universally superior product, and the pooled percentages cannot tell you which bottle to buy. If you want the strain-level detail on the yeast used in some protocols, our guide to Saccharomyces boulardii covers where that evidence sits.
Use these figures to set realistic expectations for a treatment plan your doctor has prescribed, not to choose a brand.
Gastritis Causes That Change Your Probiotic Choice
Inflammation of the stomach lining shows up the same way on a symptom list (burning, early fullness, nausea) but arrives through four very different routes. Each one changes whether a probiotic is a reasonable supportive addition at all, and which step comes first.
| Gastritis cause | Probiotic role | First step |
|---|---|---|
| H. pylori infection | Adjunct to prescribed eradication therapy; may ease side effects | Confirmatory testing and physician-directed treatment |
| Medication-related irritation | No replacement for changing or stopping a drug | Medication review with the prescriber |
| Autoimmune gastritis | Not a substitute for specialist care | Specialist evaluation and monitoring |
| Functional dyspepsia | Evidence is limited; discuss before trying | Rule out red flags and review diet and medicines |
Why the first step differs for each
H. pylori infection is the one cause where the trial data above applies directly. The probiotic rides alongside eradication therapy. It does not replace the test that confirmed the infection, and it does not replace the antibiotics. Confirm the infection first, then follow the prescriber's regimen.
Medication-related irritation is common with NSAIDs and other drugs that erode the stomach's defenses. The effective move is a medication review, because the offending drug is the cause. Adding a probiotic while continuing the irritant addresses nothing. Never stop or change a prescribed medicine on your own; bring the question to the prescriber.
Autoimmune gastritis is different in kind. The immune system attacks the parietal cells that make stomach acid and intrinsic factor, which reduces acid production and impairs absorption of iron and vitamin B12 over time. Diagnosis typically involves blood tests and endoscopy with biopsy, and monitoring matters because the condition is progressive. No probiotic substitutes for that evaluation or the nutrient monitoring that follows it.
Functional dyspepsia means symptoms without a clear structural explanation. Probiotic evidence here is thin and mixed, and the priority is ruling out the serious causes first, then reviewing diet, meal patterns and medicines.
Ask your doctor one direct question: which of these four causes do I have, and does the probiotic evidence apply to it? If the answer is "we don't know yet," the next step is testing, not a supplement.
That single question prevents most wasted spending. The cause determines whether a probiotic is a reasonable supportive addition, a pointless expense, or a distraction from something that needs treatment.
How to Judge a Probiotic Label for Gastritis
A label either gives you enough to check it against research or it doesn't. Work through these seven checks in order, and stop at any product that fails the first two.

- Named strains, with codes. The label should list genus, species and strain designation, such as Lactobacillus rhamnosus LRa66, not just Lactobacillus. A blend that gives only a total CFU number cannot be matched to any trial, so you have no way to judge it.
- Human research on that exact strain or combination. Research on a related species is not the same evidence. This is not a technicality: a 2025 review concluded that effectiveness varies by bacterial strain and by fermentation or formulation conditions, which is why brand comparisons built only on colony-forming units are weak (2025 review of strain and formulation effects).
- A dose that matches the studies. Compare the per-capsule and per-serving numbers against the research dose, not the bottle's headline figure. Serving size is where most labels mislead, because a large CFU count often comes from a three-capsule serving rather than one.
- Delivery that survives the stomach. Enteric-coated or delayed-release formats are designed to protect live bacteria from stomach acid. GutRx uses enteric-coated, acid-resistant delivery to get strains past stomach acid and into the gut intact, and our Complete formula carries 78 billion CFU across a three-capsule serving that also includes prebiotics and tributyrin.
- Third-party testing with a batch Certificate of Analysis. A COA is the only document that tells you what was in the batch you bought, rather than what the formula was designed to contain. Our products are tested by Eurofins with COAs available for download, and you can read more about how to use them in our guide to third-party tested probiotics.
- Storage instructions you can follow. Refrigerate probiotic formulas after opening, as directed. A live product handled carelessly loses viability regardless of what the label promised at manufacture.
- No disease claims. Walk away from anything that says it cures gastritis, treats H. pylori, or replaces antibiotics or acid-suppressing medicine. Those claims are the clearest signal that the marketing has outrun the evidence.
GutRx BALANCE offers 30 billion CFUs per capsule with next-gen probiotics for gut health, digestive balance, and immune support, and it lists its strains so a reader can do exactly this checking.
Why strain names are the non-negotiable
A named strain lets you search the literature, match a dose and compare products. An unnamed blend gives you nothing to verify, which is why no amount of CFU volume compensates for the omission. If a label cannot name what's inside, you cannot judge whether it applies to your situation.
What Probiotics Can and Cannot Do for Antibiotic Side Effects
Picture a standard eradication course. Within a few days the antibiotics have reshaped your gut, and the symptoms people complain about most are loose stools, cramping, nausea and a metallic taste that ruins food. That is the window where a probiotic has its most consistent, measurable effect.
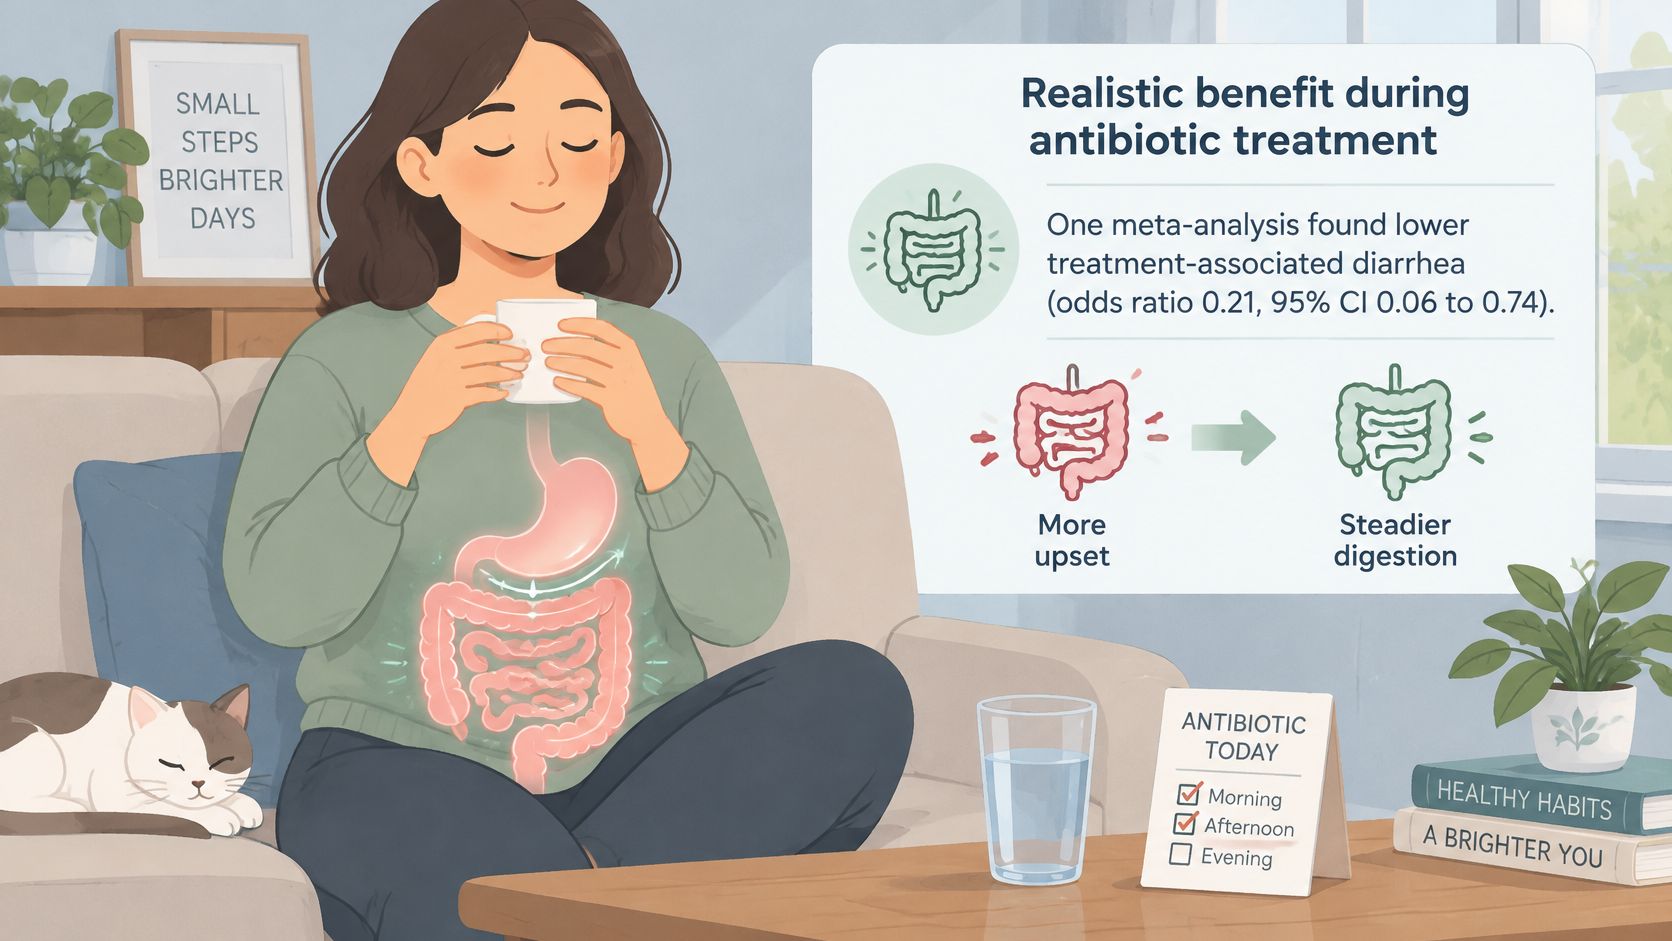
One meta-analysis found that probiotics reduced the odds of treatment-associated diarrhea to an odds ratio of 0.21, with a 95% confidence interval of 0.06 to 0.74. Overall adverse effects were also lower, at an odds ratio of 0.49 with a 95% confidence interval of 0.26 to 0.94, though the total-adverse-effect analysis showed substantial heterogeneity (I² = 85.7%), meaning the trials disagreed with each other more than usual (meta-analysis of probiotic use with antibiotic therapy).
What those numbers mean in practice
Translated: the likely benefit is comfort during eradication therapy, not cure. A wide confidence interval on the diarrhea figure tells you the true effect could be considerably smaller than the headline, and the heterogeneity figure says the pooled result hides real differences between studies, strains and populations.
Timing matters as much as the product. Take the probiotic on the schedule your prescriber or pharmacist recommends, and keep it separated from antibiotic doses by the interval they specify. If you're uncertain whether a particular strain should be spaced two hours or more from a dose, ask. The answer depends on the antibiotic and the formulation.
There's a trade-off worth naming. If a supplement helps someone finish a full antibiotic course, that has real clinical value, because adherence affects whether eradication succeeds. That is the honest case for using one. It is not a case for extra capsules when symptoms escalate. Severe or persistent diarrhea, fever, or blood in the stool needs medical attention, not a higher dose of anything.
For a fuller walkthrough of strain choices and spacing during a course, see our guide to probiotics for antibiotic use.
Red Flags That Need a Doctor, Not a Supplement
Some symptoms leave no room for choice. They indicate bleeding, ulceration, obstruction, or another condition that no live culture can treat, and the delay caused by a supplement trial is the primary risk.
- Vomiting blood, or material that looks like coffee grounds. This suggests active bleeding in the upper digestive tract.
- Black, tarry or bloody stools. Digested blood appears black; fresh blood appears red. Both need prompt assessment.
- Persistent or worsening upper abdominal pain, especially pain that wakes you at night or radiates to your back.
- Unintended weight loss, which changes the differential entirely.
- Difficulty swallowing, or repeated vomiting that keeps food down for hours.
- Signs of anemia, such as persistent fatigue, breathlessness or pallor, which can accompany slow blood loss or impaired nutrient absorption.
Anyone who is immunocompromised, seriously ill, recovering from surgery, or living with a central venous catheter should talk to a clinician before using live microbes at all. Probiotic products are generally well tolerated by healthy people, but the risk profile shifts in those groups.
Persistent nausea after eating is another symptom that deserves a proper look rather than a supplement trial, and Haven Medical's guide to post-meal nausea sets out the common triggers and the point at which they warrant investigation.
The diagnostic path is straightforward once you're in front of a clinician: a clinical evaluation, H. pylori testing when indicated, and a confirmatory test after eradication treatment. Symptom relief alone confirms nothing, because inflammation can settle before the infection clears.
Heavy vomiting of blood, or black tarry stools together with dizziness or fainting, is an emergency. Call for emergency care rather than waiting for an appointment.
Talk to Your Doctor Before Buying a Probiotic for Gastritis
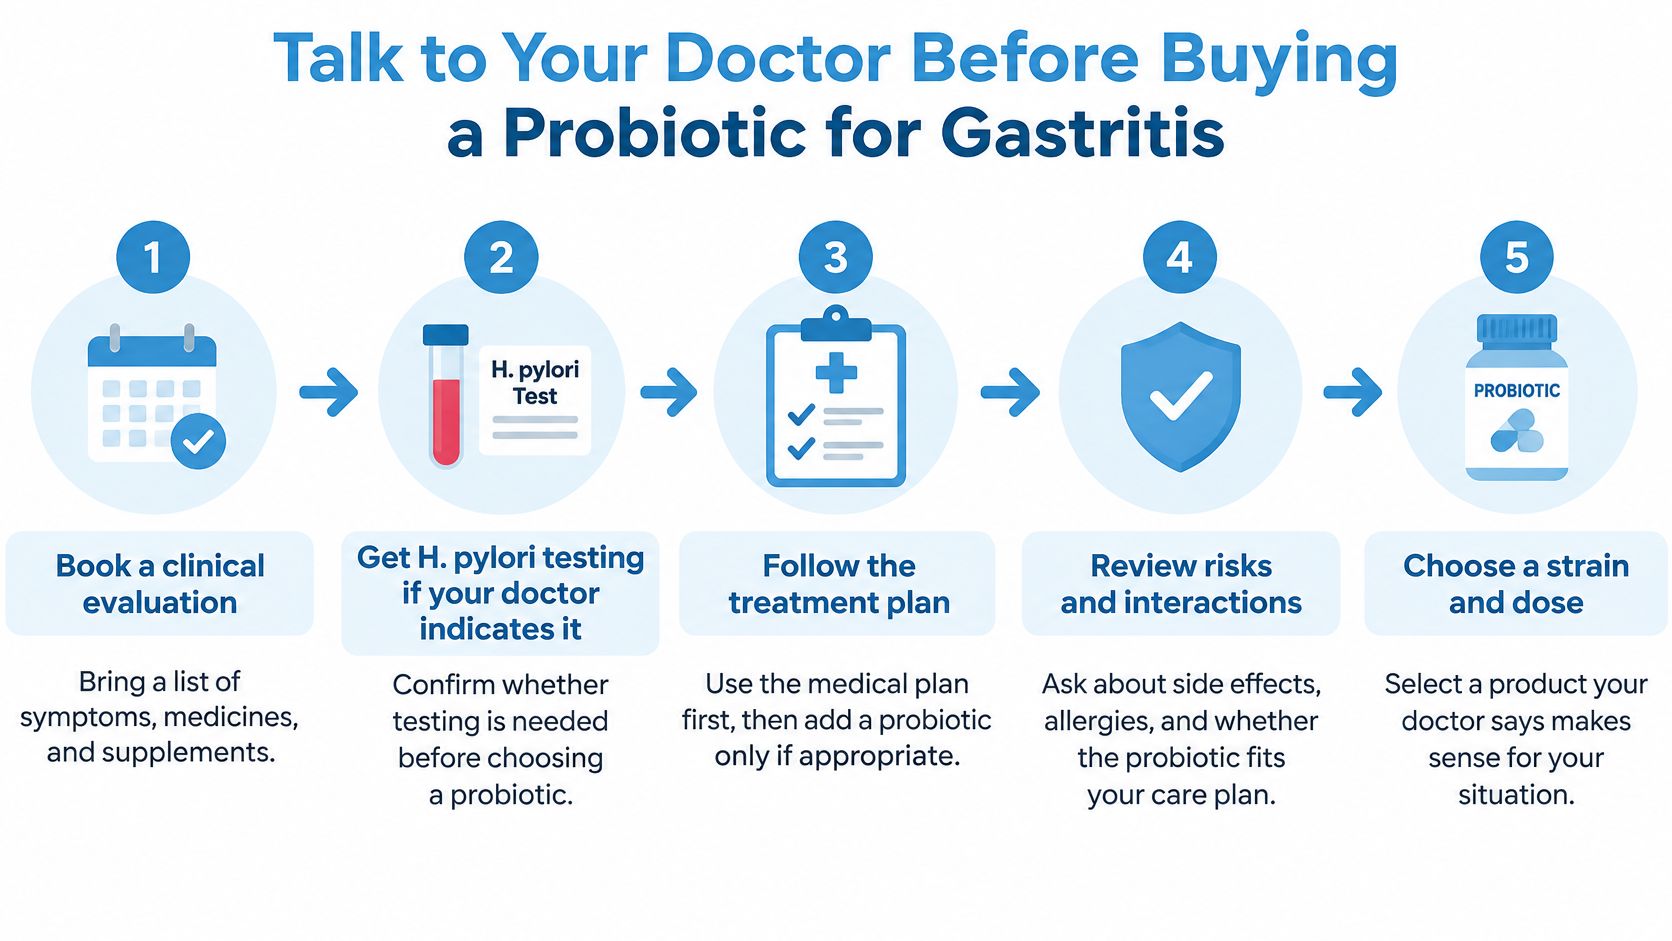
The purchase decision is the last step, not the first. Work through the sequence below in order, and treat any probiotic as an addition to a plan rather than a substitute for one.
- Book a clinical evaluation. Bring a written list of symptoms with timing and triggers, every medicine you take including over-the-counter painkillers, and any supplements already in your routine.
- Get H. pylori testing if your doctor indicates it. Testing comes before product selection, because the result determines whether eradication therapy is even part of the picture.
- Follow the prescribed eradication therapy and confirm success afterward. Ask the prescriber when to retest, since the interval depends on the regimen and on medicines such as acid suppressants that can affect results.
- Ask whether a probiotic fits as an adjunct, and which strain and dose the evidence supports for your specific situation.
- Choose a product that passes the label checks above. Named strains, matching dose, documented testing, clear storage instructions.
Where GutRx formulas fit, and where they don't
None of our products is formulated for gastritis, H. pylori or any medical condition, so your doctor's plan comes first. What we make are everyday formulas for the digestive basics, and they belong after the clinical questions are answered.
GutRx DAILY contains 10 strains and 61 billion CFU with prebiotics, taken as one capsule a day, and is designed for regularity and everyday balance. If you want a next-generation option once a plan is in place, our formulas built around Akkermansia muciniphila and Christensenella minuta (30 billion CFU per capsule) are designed for microbiome balance and the gut barrier, and Complete is the all-in-one synbiotic choice. For background on those organisms, see our articles on Akkermansia muciniphila and Christensenella minuta. For younger household members, GutRx KIDS Gummies (3-12) offer daily probiotic and prebiotic support for growing digestive systems.
These statements have not been evaluated by the FDA. These products are not intended to diagnose, treat, cure or prevent any disease.
Questions to bring to the appointment
- Which cause of gastritis do you suspect, and what test will confirm it?
- Do I need H. pylori testing, and when should I be retested after treatment?
- Would a probiotic help me tolerate this regimen, and which strain and dose do you recommend?
- Could any of my current medicines be causing this, and what are my options?
Frequently Asked Questions
Can a child take a probiotic for gastritis?
No GutRx product is formulated for gastritis, and a child with upper abdominal pain, vomiting or blood in the stool needs a pediatrician's evaluation before anything else. The KIDS Gummies (ages 3 to 12) are designed for kid-appropriate probiotic and prebiotic support, not for a stomach condition. Let the pediatrician set the plan first.
When should I retest after H. pylori treatment?
Ask the prescriber, because the timing depends on the regimen you were given and on medicines such as acid suppressants that can distort results. Symptom relief alone doesn't confirm the infection is gone. A negative result on an approved test is what closes the loop.
Should I keep taking a probiotic after the antibiotic course ends?
Follow the plan your prescriber or pharmacist gave you for both the antibiotic and the probiotic. Don't stop or extend either without asking, and don't treat a supplement as a reason to alter a prescribed schedule. If you want to continue for general digestive support, that's a separate conversation about a separate goal.
If you've worked through the clinical questions and want a quality-checked everyday formula for regularity, bloating and general digestive balance, GutRx builds synbiotics with named strains, documented doses and batch testing you can read. Our Daily, Complete and next-generation formulas are made in a GMP-certified facility in the USA, third-party tested by Eurofins with downloadable Certificates of Analysis, and backed by a 90-day money-back guarantee. Start with your doctor's plan, then visit GutRx to choose the formula that fits the goal you're working on.


